
Category: Policy

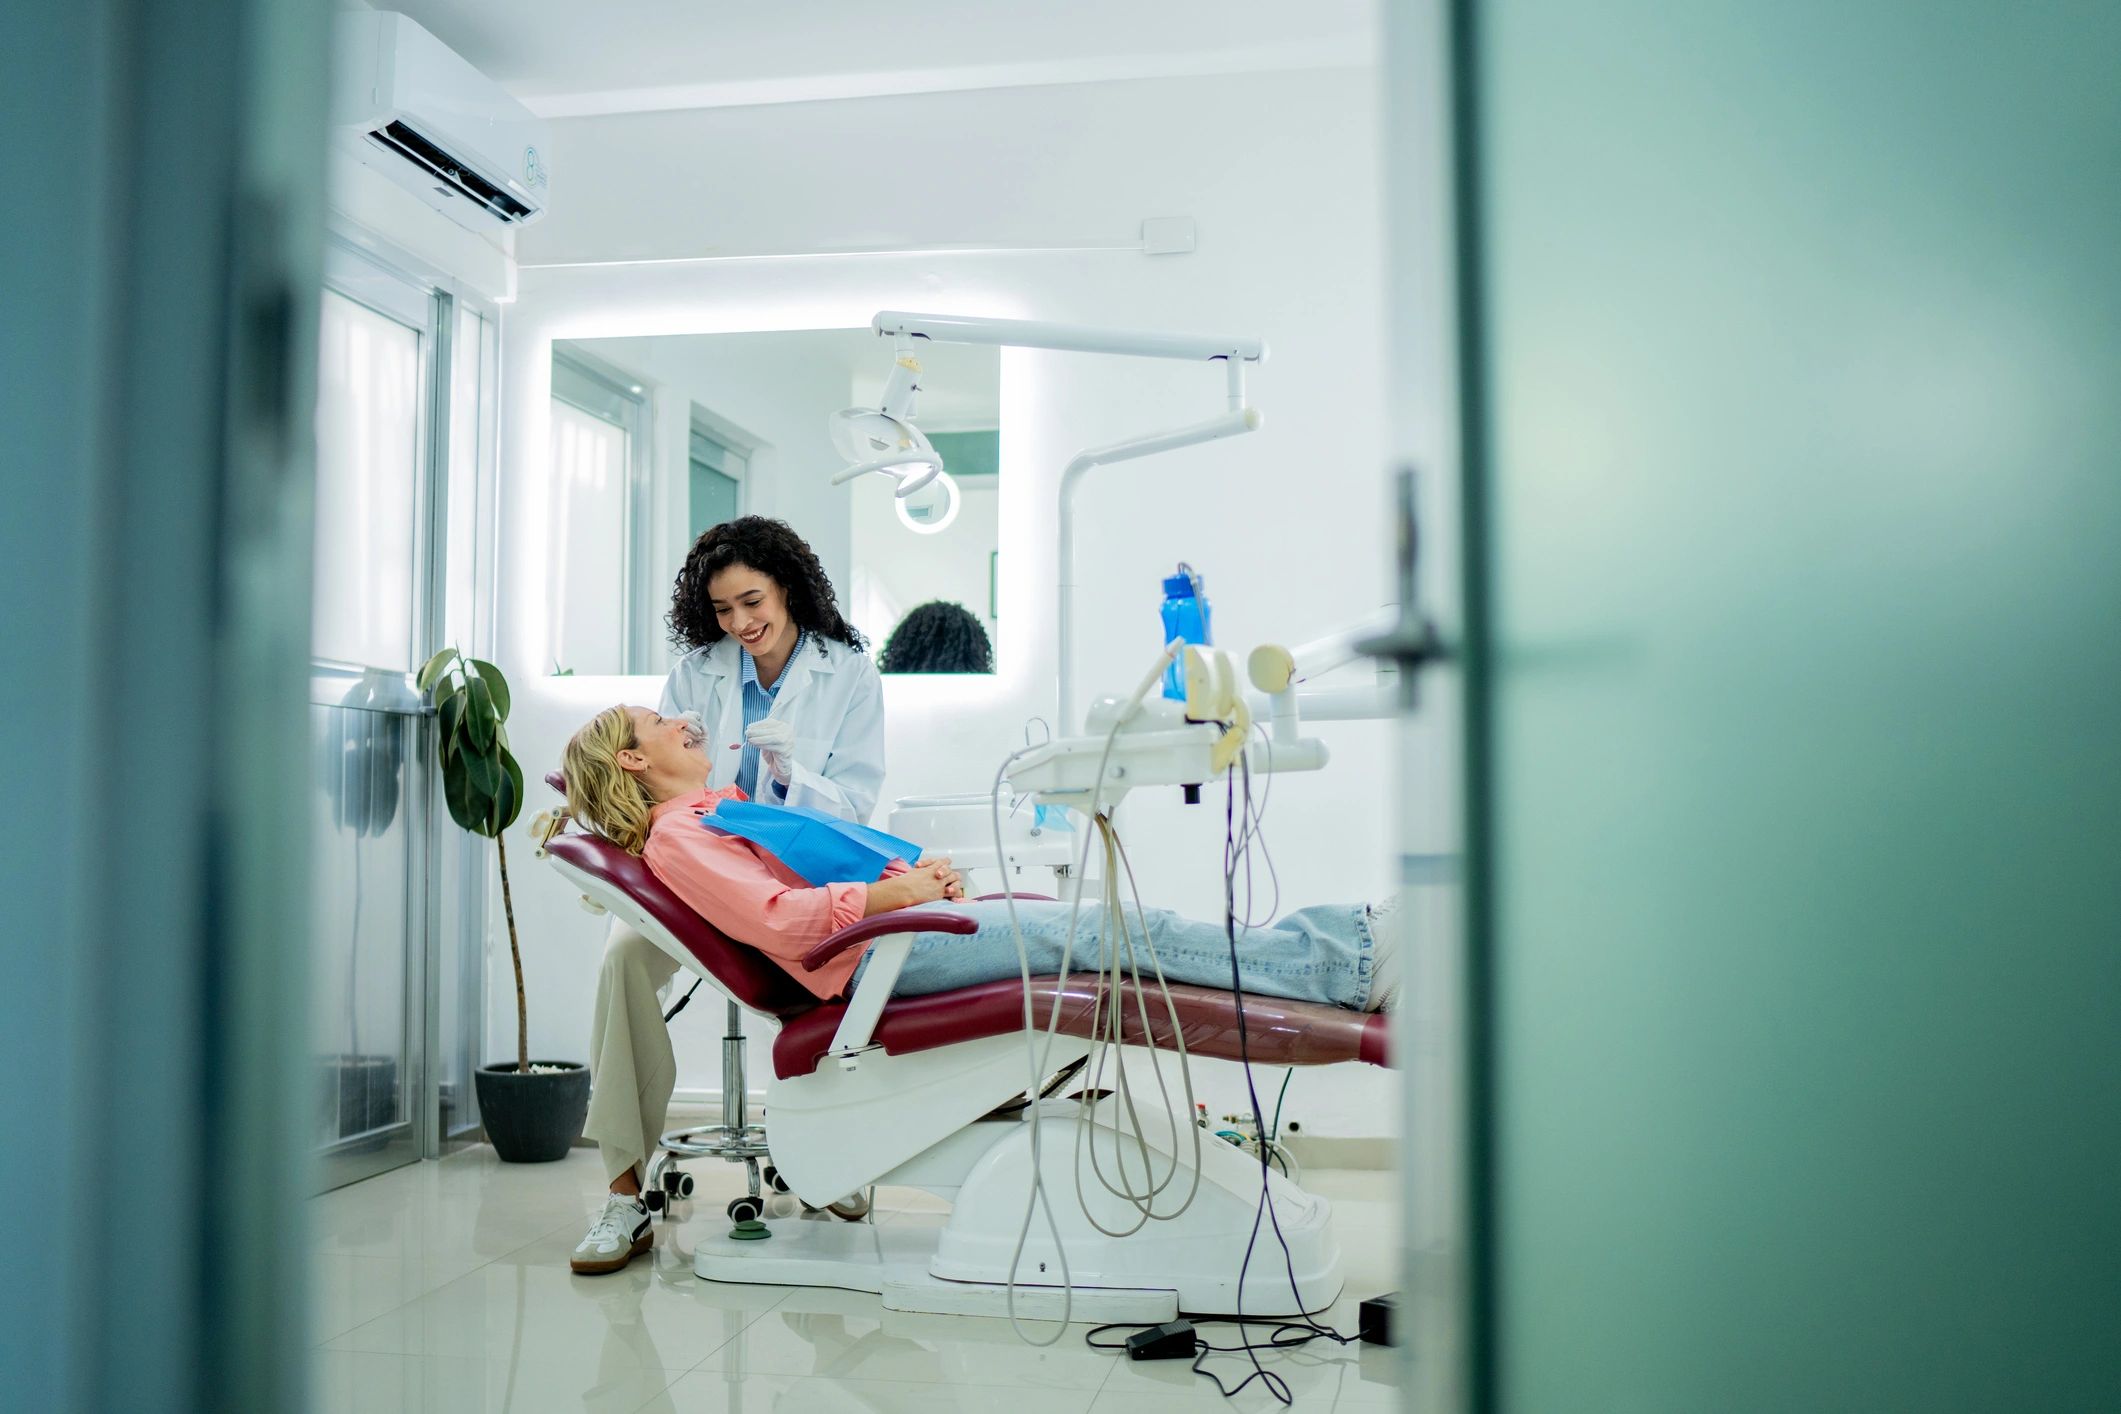
  • Canada’s Dental Care Plan Enters a New Phase: What Patients and Dentists Are Seeing in 2026

    Canada’s Dental Care Plan Enters a New Phase: What Patients and Dentists Are Seeing in 2026

    By Healthcare Reporter

    Canada’s dental-care landscape is changing rapidly.

    The federal Canadian Dental Care Plan (CDCP) has moved from a major policy rollout into an established national program serving millions of Canadians. As of August 31, 2026, more than 7.5 million unique Canadians had been enrolled in the CDCP since its launch, while 4.83 million had used their coverage to receive care during at least one benefit period, according to federal data.

    But as the program enters a new phase, the focus is shifting from who qualifies to what happens after coverage begins.

    For patients, the questions increasingly involve affordability, out-of-pocket costs and access to participating dentists. For dental professionals, concerns include reimbursement, preauthorization, administrative workload and whether Canada’s dental workforce has enough capacity to meet increased demand.

    Coverage does not necessarily mean free care

    One of the most important messages for consumers is that CDCP coverage does not mean every dental service is free.

    The federal government says the plan will help pay “a portion of the cost” of eligible oral-health services. What a patient ultimately pays depends on household income, the CDCP fee schedule, the service being provided and whether the dental provider charges more than the amount established by the program.

    The Ontario Dental Association puts the distinction plainly in its patient information: “The CDCP does not provide free dental care.”

    Patients can face co-payments and, in some circumstances, additional charges. The federal government therefore advises patients to ask their provider about potential costs before treatment.

    That distinction is becoming central to the consumer experience: having dental coverage and receiving treatment without an out-of-pocket bill are not necessarily the same thing.

    What consumers are reporting

    Early survey research suggests that many CDCP users view their experience positively.

    A Canadian Dental Association (CDA) and Abacus Data survey of 3,501 Canadians, conducted in October 2025, found that 76% of CDCP users rated their experience positively, while 78% said the program was meeting their dental-care needs. Eighty-five per cent said they had been able to continue seeing their current dentist because that dentist participates in the CDCP.

    The research also suggests that much of the care being delivered is preventive or routine, including examinations, cleanings, X-rays and fillings.

    That could prove significant over time. The impact of dental coverage should ultimately be measured not simply by the number of procedures funded, but by whether Canadians receive preventive care earlier and avoid more serious and costly oral-health problems.

    However, the survey also points to a communications challenge: some patients have expectations that the CDCP will cover their entire dental bill.

    Preauthorization creates another layer

    Some dental procedures require preauthorization before treatment can be covered.

    Health Canada’s Dental Benefits Guide states that “Certain services require preauthorization for coverage under the CDCP.”

    Preauthorization determines whether a proposed service meets the program’s coverage criteria. It does not determine whether a treatment is clinically appropriate — that remains a decision between the dentist and patient.

    For patients undergoing more complex treatment, however, the distinction can be confusing. A dentist may recommend treatment that is clinically appropriate while the CDCP determines that the procedure does not meet its reimbursement criteria.

    For dental offices, the process can mean additional documentation and administrative time.

    What dentists are saying

    The dental community’s response to the CDCP is more nuanced than simple support or opposition.

    The CDA has acknowledged the program’s potential to reduce financial barriers while identifying operational concerns involving preauthorization, administrative requirements and patient understanding of coverage.

    The association has reported that 92% of surveyed dental offices said preauthorization delays had discouraged patients from proceeding with necessary treatment, while dental-office teams reported spending an average of 32 minutes per day explaining the CDCP to patients.

    These figures come from CDA research and should be distinguished from federal administrative data. Nevertheless, they provide insight into what happens at the point of care — where program rules meet patients and dental practices.

    The CDA has called for greater predictability and transparency in preauthorization and clearer communication about coverage and costs.

    Is Canada ready for the additional demand?

    Another emerging issue is capacity.

    Expanded financial coverage can increase demand for dental services, but coverage alone does not create additional dentists, hygienists, assistants or appointment capacity.

    The CDA has identified workforce shortages as a continuing concern, particularly among dental assistants and hygienists. The association has warned that staffing constraints could affect timely access to care, particularly in rural and underserved communities.

    This creates a potential access paradox: a Canadian may qualify for the CDCP but still have difficulty finding a participating provider with capacity to accept new patients.

    What should Canadians watch next?

    The next stage of the CDCP should be measured by outcomes rather than enrolment alone.

    Key indicators include:

    • Access: Can patients find participating dentists and obtain appointments?
    • Affordability: What do patients actually pay after CDCP reimbursement?
    • Prevention: Is regular preventive care increasing?
    • Treatment: How frequently are preauthorization requests approved, denied or delayed?
    • Workforce: Can dental practices expand capacity?
    • Equity: Are rural and underserved communities benefiting equally?
    • Patient understanding: Do Canadians understand what the plan does — and does not — cover?

    These questions may ultimately tell Canadians more about the program’s success than the number of people enrolled.

    A new chapter in Canadian dental care

    The CDCP represents a major change in Canada’s approach to oral healthcare.

    Federal statistics demonstrate substantial enrolment and utilization, while survey research indicates that many users report positive experiences. At the same time, dental organizations continue to identify challenges involving preauthorization, administrative requirements, patient expectations and workforce capacity.

    Those perspectives can coexist.

    The CDCP may reduce a significant financial barrier while leaving other barriers — including geography, workforce shortages and treatment eligibility — unresolved.

    The next question for Canadian healthcare is therefore not simply whether Canadians have dental coverage.

    It is whether that coverage translates into timely, appropriate and affordable care.

    That will be the measure to watch as Canada’s national dental-care experiment enters its next chapter.

    Sources

    • Government of Canada, Canadian Dental Care Plan Statistics, August 31, 2026.
    • Health Canada, Canadian Dental Care Plan: Coverage.
    • Ontario Dental Association, Canadian Dental Care Plan FAQ.
    • Canadian Dental Association/Abacus Data, Public Opinion Data on Oral Health in Canada, 2026.
    • Health Canada, Canadian Dental Care Plan Dental Benefits Guide, 2026.
    • Canadian Dental Association, Canadian Dental Care Plan: Bridging the Gap.
    • Canadian Dental Association, Key Issues in Canadian Dentistry.

  • Canada’s Healthcare Problem Is Becoming an Economic Problem

    Canada’s Healthcare Problem Is Becoming an Economic Problem

    Canada’s healthcare debate usually focuses on familiar problems: emergency-room wait times, shortages of family doctors, surgical backlogs and overcrowded hospitals.

    All matter. But they may be symptoms of something bigger.

    Canada is spending more on healthcare while struggling to convert that spending into timely access, a healthier workforce and stronger economic productivity. As the country confronts U.S. tariffs, trade uncertainty and slower economic growth, the consequences of a strained healthcare system extend well beyond hospitals.

    The question is no longer simply what is wrong with Canada’s healthcare system?

    It is whether Canada can afford to leave it unchanged.

    More spending, more pressure

    Canada is not starving healthcare of public money.

    The Canadian Institute for Health Information (CIHI) estimates total health spending will reach approximately $399 billion in 2025, or about $9,626 per Canadian. Healthcare spending is expected to represent 12.7% of GDP.

    Yet access remains difficult. CIHI reports that Canadian emergency departments recorded 16.1 million visits in 2024–25, with half of patients waiting almost two hours to see a physician and one in 10 waiting more than five hours.

    These pressures do not originate solely in emergency departments. CIHI points to challenges throughout the system, including primary care, home care, inpatient capacity and long-term care.

    And increasingly, mental health is part of the problem.

    Mental health: the hidden economic burden

    Mental illness is often treated as a separate healthcare issue.

    Economically, that is a mistake.

    Mental health affects whether people work, how many hours they work, whether they remain attached to the labour force and how productive they are.

    The federal government estimates that mental health problems and mental illnesses cost Canada approximately $50 billion annually, including healthcare, lost work and reduced quality of life.

    The Public Health Agency of Canada similarly estimates the economic burden at approximately $51 billion a year.

    The federal government also reports that roughly 30% of disability claims are related to mental health problems or mental illness.

    The consequences can become a vicious cycle.

    Someone develops depression, anxiety, chronic pain or another disabling condition. Treatment is delayed. Their condition worsens. They leave work. Short-term disability becomes long-term disability. The healthcare system, employer, insurer and government may ultimately pay for consequences that earlier intervention might have reduced.

    Statistics Canada illustrates the scale of the challenge. In 2022, approximately 3.1 million Canadians aged 15 and older — 10.4% of the population — had a mental health-related disability.

    Among Canadians aged 15 to 24, the proportion was even higher, at 13.6%.

    This is not simply a healthcare statistic.

    It is a workforce statistic.

    The disability challenge

    Statistics Canada’s 2022 Canadian Survey on Disability found that 27% of Canadians aged 15 and older — approximately eight million people — had at least one disability, up from 22% in 2017.

    Not everyone with a disability can or should work. But there is a legitimate economic question:

    How many Canadians who want to work are being prevented from working, or from working to their full potential, because healthcare, rehabilitation, mental-health treatment, workplace accommodation and disability systems are not sufficiently connected?

    In 2024, the employment rate for Canadians with disabilities was 46.4%, compared with 66.2% for Canadians without disabilities.

    The issue is therefore not simply the cost of disability benefits.

    It is the potential economic capacity being lost when people cannot access timely treatment, rehabilitation or workplace support.

    Healthcare spending versus economic growth

    There is another warning sign.

    CIHI projects healthcare spending will grow by 4.2% in 2025, compared with estimated economic growth of approximately 2.6%.

    Healthcare spending growing faster than the economy does not automatically mean the system is unsustainable. A healthy population is an economic asset, and healthcare is an investment as well as a cost.

    But the distinction becomes important when higher spending does not consistently produce greater access, faster treatment or stronger workforce participation.

    Canada risks a cycle:

    more illness → more demand → more spending → longer waits → delayed treatment → more disability → lower workforce participation → weaker economic growth → greater fiscal pressure.

    That is the cycle Canada needs to break.

    Then came the tariffs

    The urgency is increasing because Canada’s economic environment has changed.

    The United States remains Canada’s largest trading partner, and tariffs and trade uncertainty are creating additional pressure on Canadian businesses and workers.

    The Bank of Canada has warned that tariffs could reduce Canadian economic output and slow potential growth.

    The OECD has also identified trade tensions with the United States as a significant drag on Canada’s economic outlook, while continuing to highlight Canada’s longstanding productivity problem.

    That creates an uncomfortable collision.

    Canada cannot control economic decisions made in Washington. But it can influence how effectively it uses its own workforce.

    And that puts healthcare directly into the productivity conversation.

    Health is economic infrastructure

    The OECD estimates that mental-health disorders cost OECD economies more than 4% of GDP when treatment costs and the effects of lower employment and productivity are considered.

    Canada already faces a significant productivity gap with the United States.

    At the same time, the country is dealing with an aging population, chronic disease, rising disability, mental-health pressures and healthcare workforce shortages.

    These problems reinforce one another.

    A worker unable to access timely mental-health treatment may eventually become a disability claimant.

    A claimant unable to access effective rehabilitation may leave the workforce.

    A worker leaving the workforce reduces Canada’s productive capacity.

    Lower productivity makes the economy less resilient to shocks such as tariffs.

    And weaker economic growth makes it harder for governments to finance growing healthcare and social-support commitments.

    What should Canada do?

    The answer cannot simply be spend more.

    Canada needs to become better at identifying where healthcare spending can prevent much larger downstream costs.

    That means improving access to primary care, expanding community mental-health services and integrating healthcare more effectively with rehabilitation, disability and workplace systems — while protecting privacy and individual rights.

    It also means measuring outcomes, not simply dollars spent.

    The critical question should be:

    How many Canadians could return to work, remain at work or avoid disability altogether if they received the right intervention earlier?

    That is both a healthcare question and an economic one.

    The bigger question

    Canada’s healthcare system is not failing everywhere. The OECD notes that Canada performs well on several health outcomes, including life expectancy and aspects of healthcare quality.

    The problem is that good clinical outcomes do not necessarily mean good access, integration or economic efficiency.

    Canada’s healthcare debate has spent years asking:

    How much more should we spend?

    The more important question may now be:

    What should Canadians get for every dollar we spend?

    With healthcare spending approaching 13% of GDP, approximately eight million Canadians living with a disability and mental-health costs measured in the tens of billions, the status quo deserves much greater scrutiny.

    At a time when tariffs and geopolitical uncertainty are testing Canada’s economic resilience, healthcare can no longer be treated as an isolated public service.

    It is part of Canada’s productive infrastructure.

    And healthcare reform may increasingly be one of Canada’s most important economic-policy opportunities.

    Healthcare reform is economic reform.

    Sources: Canadian Institute for Health Information; Statistics Canada; Public Health Agency of Canada; Bank of Canada; OECD; Government of Canada.